In 2020 a letter in the New England Journal of Medicine showed that Black patients were nearly three times as likely as White patients to have dangerously low blood oxygen that a pulse oximeter had missed [1]. It changed how hospitals and regulators think about a device that had been trusted for decades. It also raised an obvious question about the optical sensor on hundreds of millions of wrists.
The honest answer is more careful than either the headlines or the marketing. For some measurements, on some devices, under some conditions, skin tone makes a real difference. For others the evidence says it mostly does not. And for a surprising amount of what consumer wearables report, nobody has tested it well enough to know.
Why skin tone could matter at all
Most wearables measure heart rate with photoplethysmography, or PPG. An LED shines light into the skin, a photodiode measures how much comes back, and the small rhythmic change as blood volume rises and falls with each beat becomes a pulse [2].
Melanin absorbs light. The more melanin in the skin, the less light returns and the weaker the pulsatile part of the signal. Most wrist devices use green light because it gives a strong signal that resists motion noise, and green is also well absorbed by melanin. Red and infrared light are absorbed less [2][3]. At rest, the signal is usually strong enough for a good reading on any skin. During vigorous movement, when the algorithm has to separate a heartbeat from arm swing, the margin is smaller.
Skin tone is not the only factor. Tattoos, a loose strap, cold hands, low perfusion and higher body fat all weaken or corrupt the same signal [3][4]. That matters for how the evidence reads.
Heart rate: mostly fine at rest, less so under load
| Study | Design | Finding |
|---|---|---|
| Bent et al., npj Digital Medicine, 2020 | 53 people balanced across all six Fitzpatrick types; several consumer and research devices | No statistically significant difference in accuracy by skin tone; significant differences between devices and activities; error during activity about 30% higher than at rest [5] |
| Koerber et al., Journal of Racial and Ethnic Health Disparities, 2023 | Systematic review: 10 studies, 469 participants, 26 devices | Four studies found no skin tone effect, four found lower accuracy for darker skin, two were mixed; evidence judged inconclusive [6] |
| Hung et al., PLOS One, 2025 | 25 people, Fitbit Charge 5 against a Polar H10 chest strap | At rest, about 2.8 bpm mean error for all groups. Above 60% of heart rate reserve, about 4 bpm for lighter skin, 11.8 for medium and 11.7 for darker; significant skin tone by intensity interaction [7] |
| Kostrna et al., PLOS One, 2026 | 58 adults, Fitzpatrick III to V; Apple, Fitbit, Samsung, Garmin, calorie estimates during cycling | No robust skin tone effect on calorie error, but only 6.9% were type V; body fat had a significant effect on every device [4] |
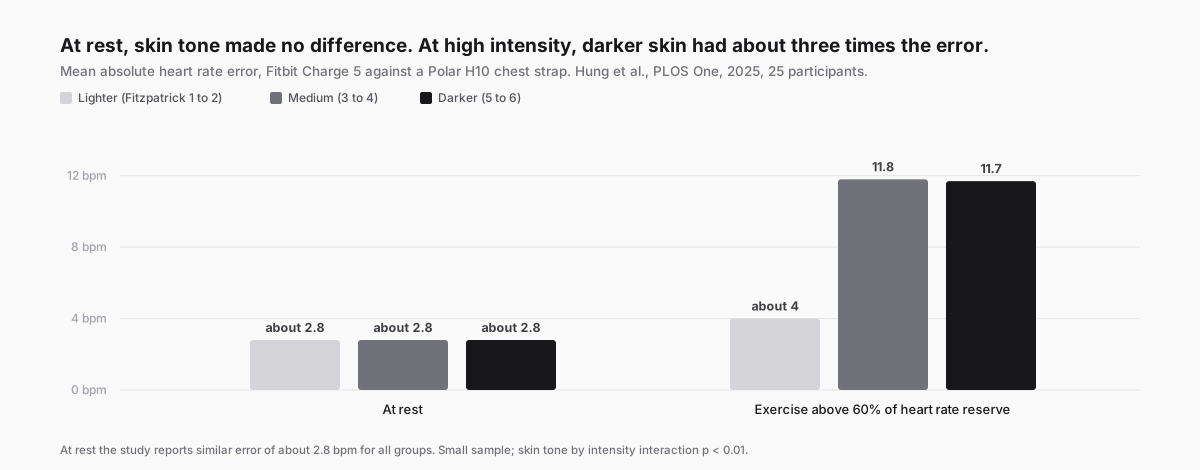
The pattern is consistent enough to state. At rest, most studies find little or no difference by skin tone. Bent’s study, the first to balance all six Fitzpatrick types, found none [5]. During hard exercise, some devices lose accuracy faster on darker skin, as Hung’s did at high intensity [7]. Differences between devices and between activities are larger than differences between skin tones in most datasets [5][6]. And every study above is small.
A note on secondary sources: at least one recent narrative review attributes large skin-tone errors to studies whose own abstracts report no significant skin-tone effect. Where a claim matters, read the primary paper.
Blood oxygen: the bias is established, the wearable evidence is thin
Pulse oximetry uses red and infrared light and the ratio between them to estimate oxygen saturation. In darker skin it tends to overestimate saturation, which is the dangerous direction because it hides low oxygen.
Sjoding and colleagues compared nearly 48,000 paired pulse-oximeter and arterial blood readings. Among patients whose oximeter read 92% to 96%, arterial oxygen below 88% occurred nearly three times as often in Black patients as in White patients [1].
The FDA responded with draft guidance in January 2025 asking manufacturers of prescription pulse oximeters to test across a wider range of pigmentation, using both the 10-shade Monk Skin Tone scale and an objective measurement called the individual typology angle, and to enrol about 150 or more participants and roughly 3,000 data points instead of around 10 people [8][9]. When researchers applied the proposed criteria to 34 fingertip and wrist oximeters in 2025, only one passed, against 22 that met the 2013 standard. Eleven showed significantly more positive bias in darker skin, and at saturations of 70% to 80% the median bias was 4.22 percentage points higher [10].
None of those 34 were smartwatches. Consumer SpO2 features use related optics, are marketed for wellness rather than diagnosis, and fall outside the pulse oximeter guidance [11]. They have been studied less across skin tones, not shown to be free of the problem. In the United States, Apple’s blood oxygen feature has also changed form twice for reasons unrelated to accuracy: it was disabled in early 2024 during Apple’s patent dispute with Masimo and restored in August 2025 with processing moved to the iPhone [12].
The bigger problem: who gets tested
The most important finding is not about any device. It is about the evidence base.
A 2026 scoping review examined 186 validation studies of consumer PPG wearables, covering 8,786 participants in 32 countries. Only 35 of them, 19%, reported participants’ skin type. In the studies that did, the median share of participants with the darkest skin types, Fitzpatrick V and VI, was 0%. The median share of adults 65 and over was also 0%, and so was the median share of people with obesity [13].
In other words, when a consumer wearable or a score built on one is described as “validated,” the typical validation study did not include anyone with the darkest skin, anyone over 65 or anyone with obesity. Manufacturers say they are addressing this. WHOOP has said it recruits across all six Fitzpatrick types and deliberately overrepresents groups where its algorithms struggle; Oura has described multi-wavelength sensing that accounts for skin tone [3][14]. Few publish results broken down by skin tone, so those remain claims. We looked at what a validation claim should contain in what it actually takes to validate a health score.
What this means for products built on wearable data
1. Validate on the people you will serve, and report by group. An average error hides a subgroup that fails. Include the full range of skin tones, record them with Monk or an objective measure alongside Fitzpatrick, and publish error by group.
2. Prefer resting and overnight signals as scoring inputs. Resting heart rate and overnight HRV are measured when the optical signal is strongest and motion is lowest, which is also where skin-tone effects are smallest. Exercise heart rate is where they grow. We explained why resting heart rate differs by device, and the same logic applies here.
3. Treat SpO2 as a trend, never a threshold. A single wearable SpO2 value should not drive an alert, a clinical recommendation or an incentive. A change against a person’s own baseline is more robust than an absolute number.
4. Use signals that are not optical. Step counts, movement, sleep timing and phone use are recorded by accelerometers and the phone itself, not by light through skin. For scores that combine behaviour and vitals, the behavioural components are indifferent to skin tone, which is a design reason to weight them, not only a coverage reason.
5. Be precise in what you claim. “Validated” without a population is a marketing word. Under the FDA’s 2026 wellness guidance, estimating and trending metrics is permitted as long as outputs are validated and not diagnostic [11]. A validation that excluded darker skin is a weak defence of a score used on everyone.
Where we sit
Sahha’s scores combine behavioural signals from the phone and wearable, such as activity, sleep timing and regularity, with physiological inputs such as resting heart rate and HRV where a device provides them. The behavioural inputs do not depend on skin tone. The physiological inputs inherit whatever error the device has, including any skin-tone effect, and we cannot correct for that downstream. We think the responsible position is to say so, weight resting and overnight measures over exercise measures, and push the industry toward stratified validation, including our own.
The short version
Optical sensors read light through skin, and melanin absorbs it. For heart rate at rest, most studies find little difference by skin tone; during hard exercise, some devices lose accuracy faster on darker skin, and device and activity effects are larger still. For blood oxygen, pulse oximeters overestimate saturation in darker skin, the FDA has proposed much stricter testing, and only one of 34 oximeters met it. Smartwatch SpO2 has barely been tested across skin tones. The deepest problem is the evidence base: in a review of 186 validation studies, the median study included no one with the darkest skin types. Validate on everyone, report by group, prefer resting measures, and treat SpO2 as a trend.
References
- Sjoding, M.W. et al. Racial Bias in Pulse Oximetry Measurement. New England Journal of Medicine, 383, December 2020. https://www.nejm.org/doi/full/10.1056/NEJMc2029240
- Photoplethysmography in Diverse Skin Tones: Evaluating Bias in Smartwatch Health Monitoring. Cureus, 17(10), 2025. https://pmc.ncbi.nlm.nih.gov/articles/PMC12592569/
- Wrist HR Accuracy: Dark Skin and Small Wrists Explained. the5krunner, June 2026, updated August 2026. https://the5krunner.com/2026/06/19/wrist-hr-accuracy-skin-tone/
- Kostrna, J. et al. Body fat, skin tone, and the accuracy of smartwatch caloric expenditure estimates. PLOS One, July 2026. https://journals.plos.org/plosone/article?id=10.1371%2Fjournal.pone.0353261
- Bent, B., Goldstein, B.A., Kibbe, W.A. and Dunn, J.P. Investigating sources of inaccuracy in wearable optical heart rate sensors. npj Digital Medicine, 3, 2020. https://pmc.ncbi.nlm.nih.gov/articles/PMC7010823/
- Koerber, D. et al. Accuracy of Heart Rate Measurement with Wrist-Worn Wearable Devices in Various Skin Tones: a Systematic Review. Journal of Racial and Ethnic Health Disparities, 2023. https://link.springer.com/article/10.1007/s40615-022-01446-9
- Hung, et al. Validity of heart rate measurements in wrist-based monitors across skin tones during exercise. PLOS One, 2025. https://journals.plos.org/plosone/article?id=10.1371%2Fjournal.pone.0318724
- FDA releases long-awaited guidance to improve accuracy of pulse oximeters for all skin tones. STAT, 6 January 2025. https://www.statnews.com/2025/01/06/pulse-oximeter-fda-draft-guidance-released/
- FDA issues much-anticipated guidance on pulse oximeters. MedTech Dive, January 2025. https://www.medtechdive.com/news/fda-draft-guidance-pulse-oximeter-accuracy/736555/
- Hughes, C. et al. Pulse oximeter performance and skin pigment: comparison of 34 oximeters using current and emerging regulatory frameworks. 2025. https://pmc.ncbi.nlm.nih.gov/articles/PMC12363702/
- Key Updates in FDA’s 2026 General Wellness and Clinical Decision Support Software Guidance. Faegre Drinker, January 2026. https://www.faegredrinker.com/en/insights/publications/2026/1/key-updates-in-fdas-2026-general-wellness-and-clinical-decision-support-software-guidance
- Apple Watch getting redesigned blood oxygen feature following legal dispute. CNBC, 14 August 2025. https://www.cnbc.com/2025/08/14/apple-watch-blood-oxygen.html
- Schipper, et al. The Representation of Different Populations in Studies Assessing the Validity of Consumer Wearable Photoplethysmography-Based Measurements: Scoping Review. JMIR mHealth and uHealth, 2026. https://pmc.ncbi.nlm.nih.gov/articles/PMC13524368/
- Oura Ring 4 could boost accuracy for diverse skin tones. Wareable. https://www.wareable.com/wearable-tech/oura-ring-4-could-boost-accuracy-for-diverse-skin-tones