Almost every step-tracking product ships with the same default: 10,000 steps a day. It is on the watch face, in the corporate challenge, in the insurance reward and in the onboarding screen. It is also the name of a 1960s gadget.
The modern research on steps is some of the most consistent in behavioural health, and it points somewhere more useful than 10,000. Benefits start far lower, rise steeply at first, and flatten well before the number most products set. For anyone designing goals, challenges or rewards around activity, the shape of that curve matters more than any single threshold.
Where 10,000 came from
In 1965 the Japanese clock and instrument maker Yamasa Tokei Keiki sold a waist-worn step counter called the manpo-kei. The name means “10,000 steps meter” [1][2]. The 1964 Tokyo Olympics had just put fitness on the national agenda, and a round, memorable target was good marketing. Walking associations formed around it, and the number travelled abroad with pedometers and, decades later, with fitness trackers [1][2].
It was never derived from a study of health outcomes. Researchers who study step counts have since described it as a figure chosen because it was round and memorable [3]. That does not make 10,000 steps harmful. It makes it arbitrary, and the research since has filled in what the arbitrary number hid.
What the evidence actually says
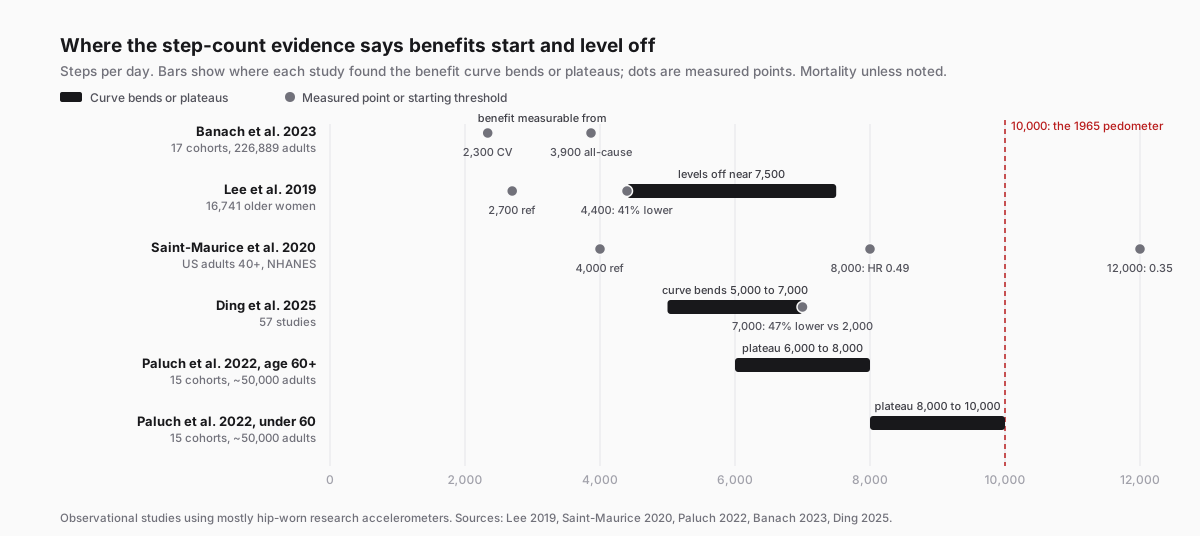
Five studies define the current picture. Each used objectively measured steps rather than self-report.
| Study | Population | Finding |
|---|---|---|
| Lee et al., JAMA Internal Medicine, 2019 | 16,741 older women | 4,400 steps associated with 41% lower mortality than 2,700; benefit levelled off near 7,500; intensity not independently associated once steps were counted [4] |
| Saint-Maurice et al., JAMA, 2020 | US adults 40 and over, NHANES | 8,000 steps associated with about half the mortality of 4,000 (HR 0.49); 12,000 with HR 0.35; cadence not significant after adjusting for total steps [5] |
| Paluch et al., Lancet Public Health, 2022 | 15 cohorts, nearly 50,000 adults | Mortality benefit levelled off at about 6,000 to 8,000 steps for adults 60 and over, and 8,000 to 10,000 for younger adults [6] |
| Banach et al., European Journal of Preventive Cardiology, 2023 | 17 cohorts, 226,889 adults | Lower mortality measurable from about 3,900 steps (2,300 for cardiovascular death); each additional 1,000 steps associated with 15% lower all-cause mortality [7] |
| Ding et al., Lancet Public Health, 2025 | 57 studies across more than ten countries | Curve bends at about 5,000 to 7,000 steps for mortality, cardiovascular disease, dementia and falls; 7,000 versus 2,000 steps associated with 47% lower mortality, 38% lower dementia and 22% fewer depressive symptoms [8][9] |
Read together, the studies agree on four things.
The curve is steepest at the bottom. Going from 2,000 or 3,000 steps a day to 5,000 carries far more measured benefit than going from 8,000 to 11,000. Banach’s analysis found benefits beginning below 4,000 steps [7].
It flattens, and earlier for older adults. Paluch’s harmonised analysis put the plateau for mortality at 6,000 to 8,000 steps for people 60 and over [6]. Lee’s cohort of older women levelled off near 7,500 [4].
Volume matters more than speed. Two independent analyses found that once total steps were counted, how fast people walked was not significantly associated with mortality [4][5]. Slow steps count.
10,000 is not wrong, just not the threshold. Some outcomes keep improving past 7,000 steps, and Ding’s review does not argue for a ceiling [8]. What the evidence rejects is 10,000 as the point at which benefit begins.
Neither of the major guidelines uses steps at all. The WHO and the US Physical Activity Guidelines recommend 150 to 300 minutes of moderate activity a week, plus strength work [10]. Steps are a convenient proxy for whether someone is meeting that, not the unit the guidance is written in.
What the studies cannot tell you
The evidence is consistent. It is also observational, and three limits matter for anyone turning it into a product.
Reverse causation. People who are already unwell walk less. Some of the association between low step counts and higher mortality therefore runs from illness to steps, not the other way. The studies adjust for health status, but imperfectly [9].
The study’s step is not your user’s step. Most large cohorts measured steps with research accelerometers worn at the hip for a week. A consumer watch on the wrist and a phone in a pocket count differently, and differently from each other; we measured how much in step counting accuracy, phone versus wrist. For older adults using a walker, a wrist device can undercount by a third [11]. “7,000 steps” in a study and “7,000 steps” on a user’s watch are close cousins, not the same number.
A week of measurement, not a lifetime. Cohorts typically measured steps over a few days and followed outcomes for years. They show that people who walked more in that week tended to fare better. They do not show that raising someone’s steps by 3,000 will produce the same difference.
None of this undermines the direction. It argues against treating any threshold, 7,000 included, as precise.
How to set step goals in an app or wellness program
Step goals are the most common health target in consumer and employer products. The research suggests six design rules, and a starting policy that follows from them.
1. Start from the user’s baseline, not a universal number. The largest benefits sit with people walking 2,000 to 5,000 steps a day. A 10,000 target tells them they fail every day. A goal of their baseline plus 1,000 or 2,000 steps is achievable and sits on the steep part of the curve. We covered how to personalise before you have much history in the cold-start problem.
2. Adjust for age. A 70-year-old at 6,500 steps is near the mortality plateau in Paluch’s analysis [6]. Congratulate them, and move the goal toward consistency or strength instead of volume.
3. Reward change over weeks, not daily pass or fail. Step counts vary with weather, work and illness. A weekly average against the person’s own trend is a better signal of behaviour change than a streak that breaks on a rainy Tuesday. The gamification evidence points the same way.
4. Do not penalise slow walking. Cadence did not predict mortality independently of volume [4][5]. A product that only credits “brisk” steps is discounting the steps older and less fit users can actually take.
5. Use the device the person has. A goal that requires a wearable excludes most adults; the phone records steps for nearly everyone who carries one without a wearable. Calibrate targets to the source, because phone and wrist counts differ.
6. Set incentive thresholds with the curve in mind. Programs that reward 10,000 steps pay the already active. UnitedHealthcare’s rewards program sets its daily goal at 5,000 [12], which puts the incentive on the steep part of the curve where the health return is largest. We looked at the wider incentive evidence in health insurance is copying auto telematics.
A starting step-goal policy
This is a default for product and program design, derived from the studies above. It is not clinical advice, and a clinician’s guidance for an individual overrides it.
| Person’s recent average | Goal to show | Why |
|---|---|---|
| Under about 5,000 steps a day | Baseline plus 1,000 to 2,000, as a weekly average | The steepest part of the benefit curve; small increases carry the largest measured gains [7][8] |
| About 5,000 to 7,000 | Move toward 7,000, then hold | Where most outcomes in the 2025 review bend [8] |
| Adults 60 and over, at 6,000 or more | Hold and add strength or balance work | Mortality benefits level off near 6,000 to 8,000 in this group [6] |
| Adults under 60, at 8,000 or more | Hold; offer intensity or variety rather than more steps | Plateau near 8,000 to 10,000 [6] |
| No history yet | A population prior for age, replaced after two weeks of data | Avoids a first-week goal that is wrong for most people |
Where we sit
Steps are one of the inputs to Sahha’s activity score. The score treats steps as a continuous factor rather than a pass or fail, so 9,000 steps still scores highly, but the reference goal it reports alongside the factor is 10,000 today. The evidence in this post is an argument we apply to ourselves as much as anyone: a score can use a population reference, but the goal a product shows a person should come from that person’s baseline and age. The number you show a user shapes what they try to do tomorrow, and a target they cannot reach is a reason to stop looking.
The short version
10,000 steps a day is the name of a 1965 pedometer, not a research result. Five major studies since 2019 agree that benefits start below 4,000 steps, rise steeply to about 5,000 to 7,000, and level off near 6,000 to 8,000 for adults over 60 and 8,000 to 10,000 for younger adults. The 2025 review of 57 studies linked 7,000 steps to 47% lower mortality than 2,000. Speed matters less than volume. The studies are observational and used hip-worn research devices, so treat any threshold as approximate. For a product, set goals from each person’s baseline, adjust for age, reward change over weeks, and put incentives where the curve is steep.
References
- No, you don’t need 10,000 steps a day. Popular Science. https://www.popsci.com/health/10000-steps-debunk-science/
- 10,000 Steps: A Brief History. Millionsteps. https://millionsteps.com/10000-steps-a-brief-history/
- Why 10,000 steps a day isn’t the secret to better health. Popular Science. https://www.popsci.com/story/health/10000-steps-evidence-study/
- Lee, I-M. et al. Association of Step Volume and Intensity With All-Cause Mortality in Older Women. JAMA Internal Medicine, 2019. https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2734709
- Saint-Maurice, P.F. et al. Association of Daily Step Count and Step Intensity With Mortality Among US Adults. JAMA, 323(12), 2020. https://jamanetwork.com/journals/jama/fullarticle/2763292
- Paluch, A.E. et al. Daily steps and all-cause mortality: a meta-analysis of 15 international cohorts. Lancet Public Health, 7(3), 2022. https://www.thelancet.com/journals/lanpub/article/PIIS2468-2667(21)00302-9/fulltext
- Banach, M. et al. The association between daily step count and all-cause and cardiovascular mortality: a meta-analysis. European Journal of Preventive Cardiology, 30(18), 2023, with corrigendum. https://academic.oup.com/eurjpc/article/30/18/1975/7226309
- Ding, D. et al. Daily steps and health outcomes in adults: a systematic review and dose-response meta-analysis. Lancet Public Health, 10, August 2025. https://www.thelancet.com/journals/lanpub/article/PIIS2468-2667(25)00164-1/fulltext
- Expert reaction to systematic review and meta-analysis of daily step count and risk of chronic diseases, cognitive decline and death. Science Media Centre, July 2025. https://www.sciencemediacentre.org/expert-reaction-to-systematic-review-and-meta-analysis-of-daily-step-count-and-risk-of-chronic-diseases-cognitive-decline-and-death/
- WHO guidelines on physical activity and sedentary behaviour: at a glance. World Health Organization, 2020; and Adult Activity: An Overview, CDC. https://www.who.int/europe/publications/i/item/9789240014886 and https://www.cdc.gov/physical-activity-basics/guidelines/adults.html
- Why your smartwatch may be misleading your doctor: a cross-sectional study on the impact of mobility aids on wearable accuracy in older adults. PeerJ. https://peerj.com/articles/20690/
- UnitedHealthcare Introduces New Rewards Program With a Modern Approach to Well-Being. UnitedHealth Group, 8 February 2023. https://www.unitedhealthgroup.com/newsroom/2023/2023-02-08-uhc-introduces-rewards-program-well-being.html